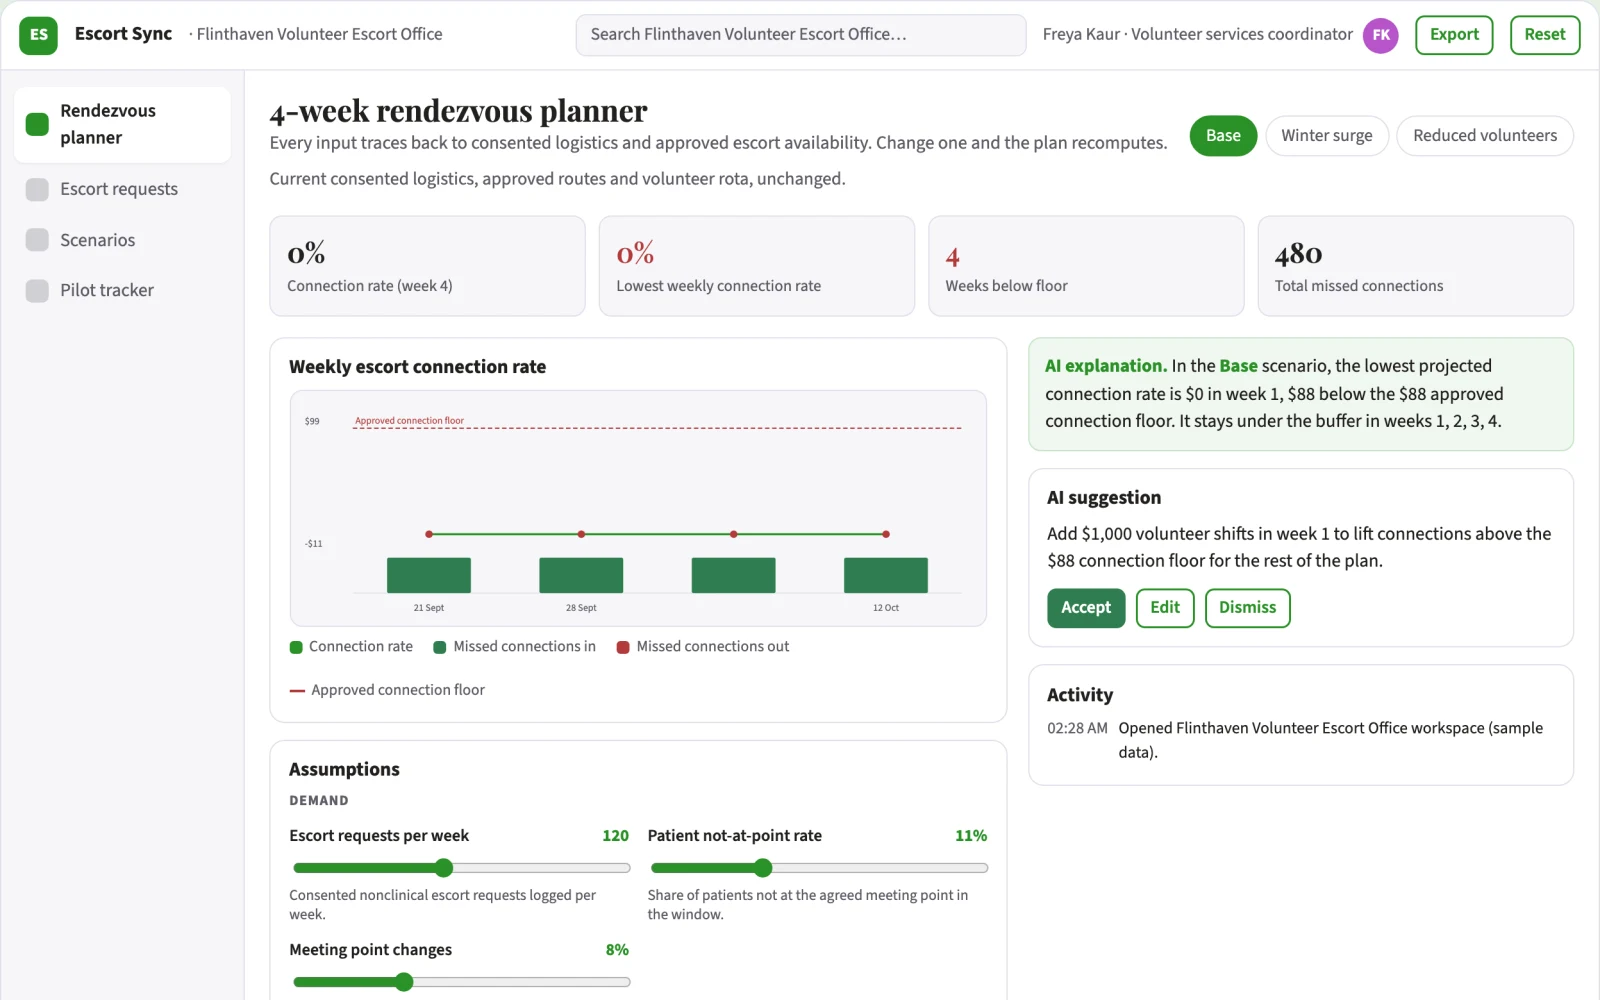
Outpatient escort rendezvous coordinator
Reduce missed escort connections and administrative calls.
- For
- Hospital volunteer services arranging nonclinical escorts within a facility
- Solves
- Patients and escorts miss each other because changing arrival points and appointment times are coordinated by phone.
- Delivers
- Coordinator-approved escort assignment with consented arrival instructions
- Built in
- about 6 weeks of creation time, MVP in 7 days
- Investment
- $25,000 for the MVP, $50,000 for the full product
- Run it
- Inside your business, or as part of your offer to clients
What it does
Reduce missed escort connections and administrative calls.
- Match nonclinical escort requests to approved volunteers.
- Suggest accessible meeting and handoff windows.
- Escalate missed rendezvous to the coordinator.
- Compare the reviewed result with the recorded baseline and value assumptions.
- Capture corrections and named-owner approval before consequential use.
- Export a versioned coordinator-approved escort assignment with consented arrival instructions with source references and unresolved questions.
What goes in, what comes out
- Consented appointment logistics
- Patient-selected meeting points
- Approved routes
- Escort availability

AI drafts, people review. Assumption-driven planning and decision workspace.
- Coordinator-approved escort assignment with consented arrival instructions
How it works
The workflow
- InStart with
Consented appointment logistics, patient-selected meeting points, approved routes and escort availability
- 1
Confirm the buyer's problem and scope
- 2
Collect consented appointment logistics
- 3
Patient-selected meeting points
- 4
Approved routes and escort availability
- 5
Then follow this sequence: 1
- OutFinish with
Coordinator-approved escort assignment with consented arrival instructions
AI does the heavy lifting, people stay in charge
Use AI to interpret permitted inputs, suggest structured mappings and generate candidate outputs for the three stated task modules. Use deterministic code for arithmetic, schema validation, hard constraints and reproducible tests. Review source-linked explanations and uncertainty before accepting results. One facility; volunteers provide nonclinical assistance only and staff determine any clinical transport need. A model suggestion is never a verified fact, professional decision or authorization to act.
What your team sees
Primary screens: Constraint and input setup, Scenario comparison, Decision and pilot tracker. Place editable drivers and constraints beside a clearly labeled scenario output. Include a baseline view, comparison chart or schedule, and an assumptions history. Let users trace a proposed quantity or date back to its inputs. Keep forecasts distinct from actual results. Make the task-specific outcome coordinator-approved escort assignment with consented arrival instructions visible beside its evidence, review state and value baseline.
Accounts and administration
Scenario versions, baseline reconciliation, constraint checks, assumption ownership, reviewer approvals, plan exports and actual-versus-plan tracking. Add organization access boundaries, named reviewers, usage caps, data retention controls, export logs and explicit approval for external actions.
Integrations and data access
Clinic-approved content and administrative exports. Clinical integrations require separate assessment. Read-only operational exports, calendars and finance or inventory records as relevant. Start with plan exports and retain human approval for execution. Start with authorized file exchange. Validate current provider access, usage rights and schema behavior before promising a connector.
How we build it
We build with our own AI software development factory, so most implementations take days to a few weeks of creation time, not months. You see working software at every step, and exact timing depends on availability.
- 1
Scoping call
Day 1Thirty minutes on your process, your data and how you want to run it: for your own team, or for your clients. You get a fixed scope and price for the MVP.
- 2
MVP
7 daysOne buyer segment, one recurring use case; first modules: match nonclinical escort requests to approved volunteers; suggest accessible meeting and handoff windows. Manual review in the loop. Built by our AI software factory.
- 3
Paid pilot
8 daysAccounts, roles, review states, audit trail and the first integration, hardened for two to three paying pilot customers.
- 4
Full product
3 weeksSelf-serve onboarding, billing, monitoring and the wider integration set.
- 5
Run and improve
MonthlyWe host, monitor and improve it for a fixed monthly fee, or hand it over to your team. How the retainer works.
Why we start with an MVP
An MVP, or minimum viable product, is the smallest version that your users can actually work with. It is not a cheap version of the full solution. It is a test, built to answer the questions that decide whether the rest is worth building.
- Pick the riskiest assumption. Here: will hospital volunteer services arranging nonclinical escorts within a facility use it to solve "patients and escorts miss each other because changing arrival points and appointment times are coordinated by phone"?
- Build only what tests it. One team, one use case, a few core modules. People do the rest by hand for now.
- Run a paid pilot. Agree quality and outcome thresholds before the pilot using this measure: Completed requested escorts and coordinator minutes per rendezvous without increased patient delay.
- Measure, then decide. Track completed requested escorts and coordinator minutes per rendezvous without increased patient delay; accepted-output rate; material error rate; reviewer correction time; actual repeat purchase. Then expand, change course or stop, with evidence instead of opinions.
MVP scope for this solution. Pilot scope: One facility; volunteers provide nonclinical assistance only and staff determine any clinical transport need. Implement one approved input format, a bounded representative case set and the first two task modules: match nonclinical escort requests to approved volunteers; suggest accessible meeting and handoff windows. Support the third module with operator review: escalate missed rendezvous to the coordinator. Include source references, corrections, basic organization access, approval states, export and value measurement. Use managed operator assistance for unresolved exceptions. The cost estimate covers this narrow prototype, not unrestricted multi-tenant scale, complex production integrations, specialist certification or physical operations.
After the MVP. Once paid pilots prove usefulness, automate repeatable reviewed steps and add one verified source integration. Expand supported inputs and case volume only after new evaluation cases pass. Build reusable customer configurations and recurring value reports around coordinator-approved escort assignment with consented arrival instructions. Retain the explicit scope boundary: One facility; volunteers provide nonclinical assistance only and staff determine any clinical transport need.
What the build depends on. A defensible calculation model, explicit units, constraint validation and representative boundary tests. Advanced forecasting or optimization needs adequate historical data. Obtain representative authorized cases, baseline measurements, qualified reviewers and a buyer-side decision owner. Specific limitation: One facility; volunteers provide nonclinical assistance only and staff determine any clinical transport need.
Investment
A planning range to start the conversation, not a quote. You pay per phase, so you can stop after the MVP.
- Phase 1
MVP
One buyer segment, one recurring use case; first modules: match nonclinical escort requests to approved volunteers; suggest accessible meeting and handoff windows. Manual review in the loop.
- Phase 2
Paid pilot
Accounts, roles, review states, audit trail and the first integration, hardened for two to three paying pilot customers.
- Phase 3
Full product
Self-serve onboarding, billing, monitoring and the wider integration set.
Indicative total, MVP to full product$50,000about 6 weeks of creation time · start with the MVP from $25,000
Running costs per month
A rough indication of monthly hosting and AI model costs once it is live, not tested. Real costs depend on usage, file sizes and the models chosen.
| Stage | Hosting and infrastructure | AI usage | Total per month |
|---|---|---|---|
| MVP and paid pilotabout 3 customers | $50–$100 | $50–$100 | $100–$200 |
| Full productabout 50 customers | $190–$380 | $350–$700 | $540–$1,080 |
Run it or resell it
For your own team
Hospital volunteer services arranging nonclinical escorts within a facility run it inside the business: consented appointment logistics, patient-selected meeting points, approved routes and escort availability in, coordinator-approved escort assignment with consented arrival instructions out, reviewed by your people.
As part of your offer
Agencies, consultancies and software companies can offer it to their own clients under their brand. We build and maintain it; you sell and deliver it.
Your brand, or this one
Run it under your own brand, or start from this concept style.
- primary
#2a9127 - accent
#b654c9 - surface
#e5f1e4 - ink
#22201e
- Headings
- Playfair Display
- Text
- Source Sans 3
- Voice
- Careful, kind, clinically plain
Selling it to your own clients: the go-to-market playbook
Pricing to test
Test USD 750-3,000 for a scoped planning setup and review, then USD 200-900 monthly for refreshes within agreed complexity. Data integration and optimization are separately scoped. All ranges are hypotheses. Package the initial sale as one bounded coordinator-approved escort assignment with consented arrival instructions. Recurring fees must specify volume, review depth and integration support. For exchanges, test a disclosed coordination or successful-service fee rather than holding customer funds. Reprice only after measuring real delivery labor; platform-build cost is separate from a commercial pilot fee.
Message to test
Reduce missed escort connections and administrative calls. Demonstrate a concrete coordinator-approved escort assignment with consented arrival instructions using the buyer's approved example and show the baseline, corrections and actual delivery effort.
Where to find buyers
Hospital volunteer services arranging nonclinical escorts within a facility professional communities; specialist consultants serving this buyer; permissioned partner introductions; practical demonstrations at relevant trade or practitioner events.
Lead magnet
A reviewed sample coordinator-approved escort assignment with consented arrival instructions from a small authorized input set, with a transparent calculation of completed requested escorts and coordinator minutes per rendezvous without increased patient delay and no promised savings.
The first 30 days
- Week 1: interview five hospital volunteer services arranging nonclinical escorts within a facility and inspect a recent example of patients and escorts miss each other because changing arrival points and appointment times are coordinated by phone.
- Week 2: prepare a consented or synthetic demonstration of the three task modules.
- Week 3: seek one bounded paid pilot with agreed baseline and acceptance criteria.
- Week 4: measure completed requested escorts and coordinator minutes per rendezvous without increased patient delay, reviewer effort and repeat-purchase interest. This is a demand-validation plan, not a thirty-day full-product delivery promise.
Paid pilot
Agree quality and outcome thresholds before the pilot using this measure: Completed requested escorts and coordinator minutes per rendezvous without increased patient delay. Continue only if the buyer accepts the actual output, the intended job outcome improves without unacceptable errors, and measured delivery cost fits willingness to pay. Revise or stop if access is unavailable, qualified review cannot be provided, or apparent savings disappear after corrections and support. Use held-out cases when comparing model quality; use a properly reviewed comparison design before making causal claims. Record missing cases and negative results alongside successful outputs.
Success metrics
Completed requested escorts and coordinator minutes per rendezvous without increased patient delay; accepted-output rate; material error rate; reviewer correction time; actual repeat purchase.
Retention and expansion
Repeat the workflow when the buyer again needs coordinator-approved escort assignment with consented arrival instructions. Retain permissioned settings and reviewed examples, report realized value honestly, and sell increased volume or adjacent approved workflows only after contribution margin and quality remain acceptable.
Why clients would pick it
A validated domain model, customer-approved constraints and forecast or decision history that improves practical planning. Build a permissioned library of representative task cases, reviewer corrections and verified operating constraints for hospital volunteer services arranging nonclinical escorts within a facility. Repeatable delivery and useful integrations matter more than access to a base model.
Alternatives and positioning
Spreadsheets, planners, specialist forecasting tools and existing scheduling or configuration software. Compare this product with the buyer's present method on completed requested escorts and coordinator minutes per rendezvous without increased patient delay. Offer a bounded paid workflow instead of claiming broad autonomous expertise. Market uniqueness and competitor coverage are not verified.
Main delivery costs
Data preparation, domain modeling, validation, scenario computation, reviewer support and ongoing assumption maintenance. Additional initial validation requires representative authorized sample preparation, buyer interviews, qualified domain review and bounded validation of coordinator-approved escort assignment with consented arrival instructions. Track cost per accepted output, including correction work, unsuccessful cases and support.
Safeguards
Begin with administrative scope or clinician-reviewed material. Minimize sensitive patient data, restrict access and obtain required organizational review before connecting clinical systems. One facility; volunteers provide nonclinical assistance only and staff determine any clinical transport need. Keep all consequential actions under authorized human control and do not fabricate missing inputs, permissions, professional judgments or market evidence.